
CJC-1295 + Ipamorelin: The Clean GH Stack Explained
Written against the cited studies. Last updated 7 Oct 2026
Key takeaways
CJC-1295 plus ipamorelin is the classic way to get your body to release more of its own growth hormone. People use it for deeper sleep, better recovery and, over time, a leaner body. It is a research pairing of two growth hormone secretagogues. A secretagogue is something that prompts a gland to release its own hormone. CJC-1295 raises how much GH a pituitary cell can release per pulse. Ipamorelin triggers that pulse. They act on separate receptors in the same cell. Switching on both gives a bigger GH release than either one alone, and more than the two added together.
If you have spent any time around growth hormone peptides, you have come across this pair. CJC-1295 and ipamorelin are the classic GH stack. They quietly replaced the older, messier combinations the bodybuilding world used to run. People treat the pair as a single product, and for good reason: you almost never want one without the other.
In short, these two peptides tell the pituitary to release more of your body's own growth hormone. They come at it from two different angles at once, and the two angles add up to more than the sum of their parts. It is not injected HGH. And the selective version of the stack triggers GH release without the cortisol, prolactin and strong hunger linked to the older peptides of this type.
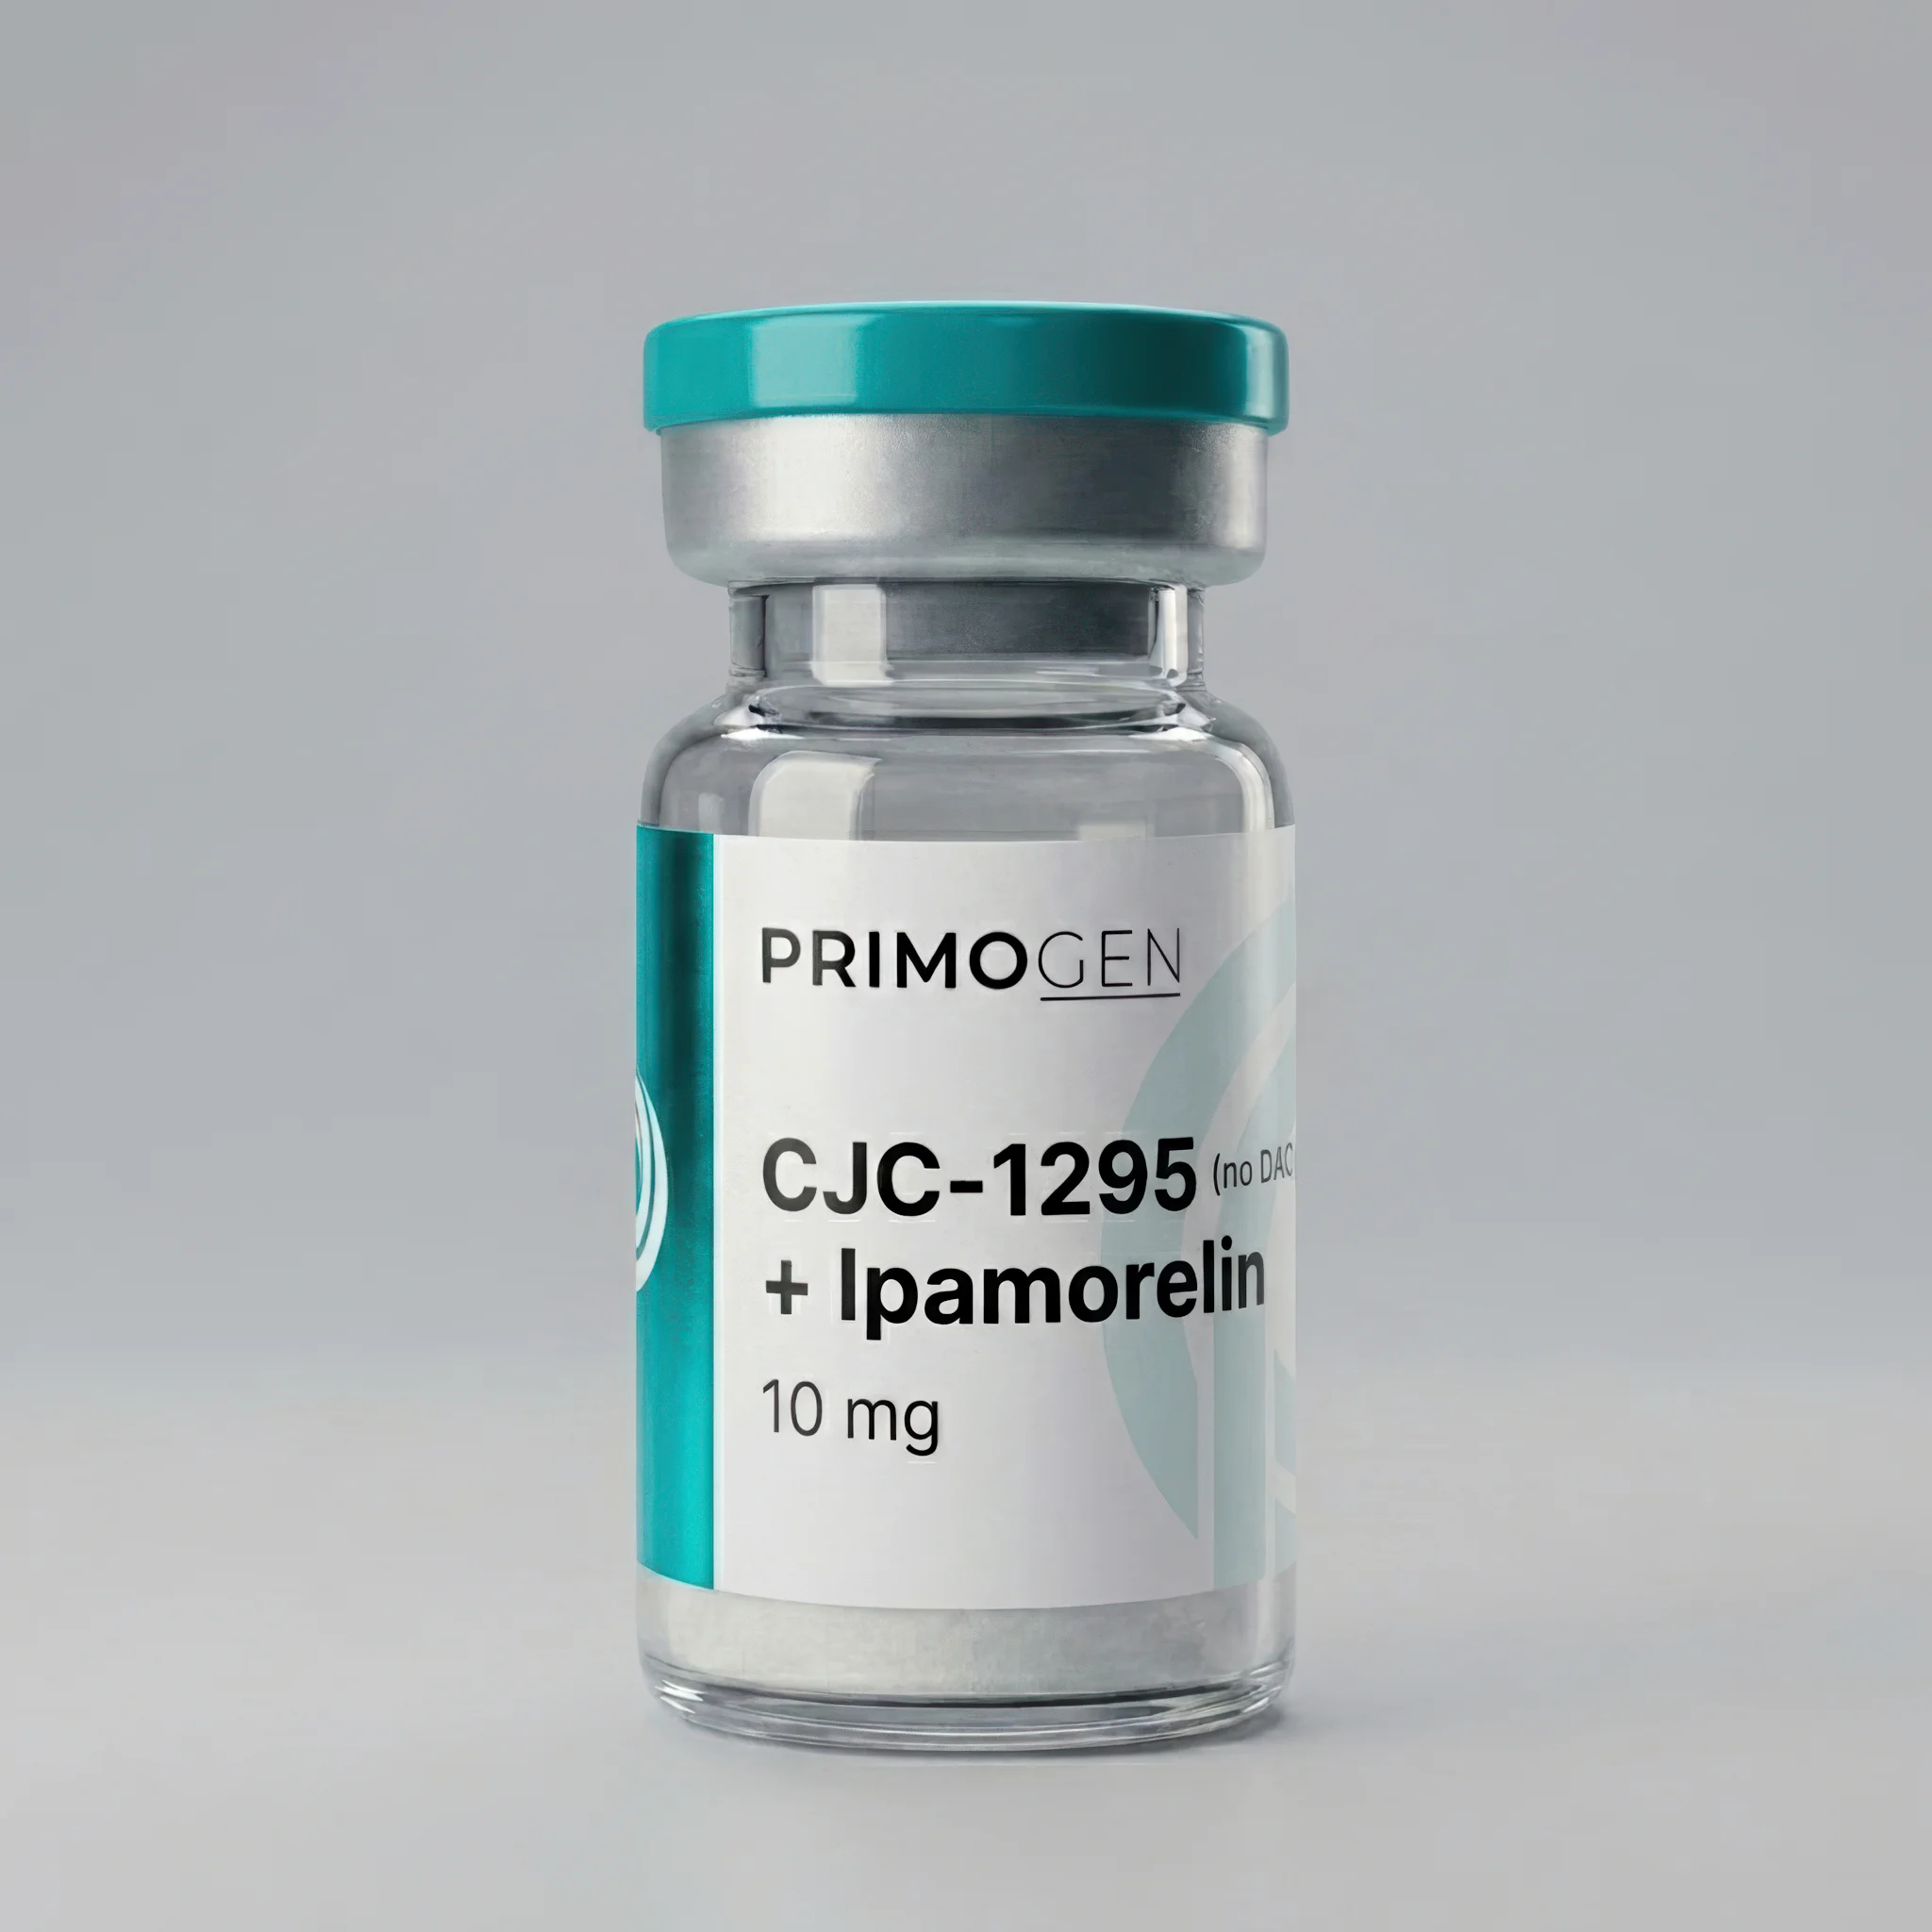
A word on where Primogen sits. We carry CJC-1295 and ipamorelin as standalone vials, and as a pre-mixed CJC-1295 + ipamorelin blend, since the blend is how most people use it. All of it is sold as research material. This guide explains how the stack works, and what the evidence does and does not yet cover.
What does the CJC-1295 + ipamorelin stack actually do for you?
Here is what people report, in everyday terms, and roughly when.
- The first week: sleep. Deeper, more vivid sleep is usually the first thing people notice, often within 3 to 7 nights.
- Weeks 2 to 4: recovery. Users report bouncing back faster from training, and muscles that look and feel fuller. Some of that fullness is water.
- Weeks 4 to 12: body composition. Users describe modest gains in lean muscle and a little fat loss. No published study has measured this for the stack yet, so treat it as user reports.
What not to expect: steroid-like size or fast results. It works through your body's own growth hormone, so the effect is gradual and stays within a natural range. How much you get also depends on how well your own pituitary gland responds.
A few things can go the other way. A brief head rush or flushed face just after injecting is common, and it passes within minutes. Some people feel a bit sluggish in the first week. Water retention and tingling in the hands can show up, mostly at higher doses.
How do CJC-1295 and ipamorelin compare side by side?
CJC-1295 (no-DAC) copies GHRH and sets the size of the pulse. Ipamorelin switches on the ghrelin receptor (GHS-R1a) and triggers the pulse. Ipamorelin has a longer half-life, meaning it takes longer for half of it to clear from the body. It also causes no cortisol or prolactin spillover. The table compares the two, including the typical community dose.
| CJC-1295 (no-DAC) | Ipamorelin | |
|---|---|---|
| Class | GHRH analog (a lab-made copy of GHRH) | GHRP / ghrelin mimic (GHS-R1a agonist) |
| Receptor | GHRH receptor | Ghrelin receptor (GHS-R1a) |
| Role in the stack | Raises pulse size (the "ceiling") | Fires the pulse (the "trigger") |
| Half-life | ~30 min (no-DAC); 5 to 8 days (with DAC) | ~2 hours |
| Cortisol / prolactin spillover | None on its own | None, even far above the GH-active dose |
| Hunger | Very little | Minimal (far less than GHRP-6) |
| Typical community dose | 100 mcg per shot | ~100 mcg saturation dose per shot |
| Route | Sub-Q (under the skin) | Sub-Q (under the skin) |
| Stocked by Primogen | Yes | Yes |
For the wider family this stack belongs to, and how these peptides differ from injecting GH directly, see GH secretagogues explained.
How does the CJC-1295 + ipamorelin stack actually work?
Both peptides raise GH output from the pituitary, but they get there through two different receptors. CJC-1295 binds the GHRH receptor to raise the size of the pulse. Ipamorelin binds the ghrelin receptor to trigger the pulse. Switching on both at once gives a GH release bigger than the two added together.
CJC-1295 copies GHRH. GHRH (growth hormone releasing hormone) is the signal your brain normally sends to the pituitary. It tells the pituitary to make and release GH. CJC-1295 is a lab-made, longer-lasting version of that signal. It binds the GHRH receptor and switches on a messenger pathway inside the cell (cAMP/PKA). That turns up the GH gene and primes the cell to release a bigger pulse (Jetté et al. 2005). On its own, it raises the size of GH release, meaning how much comes out per pulse. But it does not strongly trigger the pulse itself.
Ipamorelin is a GHRP that copies ghrelin. A GHRP (growth hormone releasing peptide) is a peptide that triggers a GH pulse. Ipamorelin does it by copying ghrelin, the stomach's hunger hormone. It binds a different receptor entirely, the ghrelin receptor (GHS-R1a). That sets off a calcium-driven chain reaction inside the same pituitary cell. The result is a pulse of stored GH pushed out the door. It also eases off somatostatin, the "brake" that normally holds GH back. So ipamorelin is the trigger.
Put them together. One peptide raises the ceiling and the other pulls the trigger. They work through separate receptors and separate signals inside the very same cell. Switching on both gives a GH release bigger than the two added together. In pig studies, the total GH output was roughly two to four times that of either compound alone (Jorgensen et al. 2001). In healthy men, GHRH and a GHRP given together gave a clear boost in GH release at below-maximum doses (Bowers et al. 1990). This is the closest a drug pairing gets to the natural teamwork of ghrelin and GHRH that drives GH pulses at night.
In short: CJC-1295 sets how big the pulse can be. Ipamorelin makes the pulse happen. Doing both at once gets you more GH than the two added separately.
CJC-1295 with DAC vs without DAC: which one belongs in the stack?
For the classic ipamorelin stack, the answer is CJC-1295 without DAC. The two forms behave like two different compounds. The DAC version lasts for days and gives a steady "GH bleed". The no-DAC version clears in about 30 minutes. It gives a short, sharp pulse that lines up with ipamorelin's own pulse.
CJC-1295 with DAC carries a "Drug Affinity Complex". This binds it to albumin, a protein in the blood. That stretches its half-life out to roughly 5.8 to 8.1 days (Teichman et al. 2006). One injection keeps the GHRH signal raised for most of a week, a steady "GH bleed". That is handy, since you dose once a week. But it trades away the natural pulse pattern for a more constant level.
CJC-1295 without DAC is also sold as Modified GRF 1-29 or Mod GRF 1-29. Its half-life is about 30 minutes. It briefly boosts a single GH pulse and then clears. This is the version that pairs cleanly with ipamorelin's own short pulse. It is the one most people mean by "the stack". Taken just before sleep, the pulse lines up with the body's natural night-time GH surge.
Which to choose comes down to approach. The no-DAC form keeps GH release pulsatile, meaning it comes out in bursts rather than a steady stream. That is how the GH system (the chain of hormone signals from brain to pituitary) evolved to work. It is also linked to keeping the somatostatin feedback loop intact. Long-acting forms like the DAC version raise GH without fully keeping that burst pattern (Ionescu & Frohman 2006). The performance and longevity community leans heavily toward no-DAC plus ipamorelin for that reason. Primogen's blend uses the no-DAC form with ipamorelin, because that is the setup the stack was built around.
Why ipamorelin instead of the older GHRPs?
Ipamorelin is favoured because it is selective. It releases GH without the cortisol, prolactin and strong hunger linked to the earlier GHRPs. GHRP-6, GHRP-2 and hexarelin came before it, and all of them release GH. But GHRP-6 is linked to strong hunger. GHRP-2 and hexarelin are linked to raised cortisol and prolactin alongside the GH.
Its key trait, shown in the very first studies, is this selectivity. Raun et al. (1998) described it as the first of its type to be as selective for GH as GHRH itself. They reported that it did not meaningfully raise cortisol, or ACTH (the pituitary signal that drives cortisol). That held even at doses more than 200 times the dose needed to release GH. This is why it replaced the older GHRPs. You get the GH pulse without the stress-hormone spillover or hunger spike seen with the others. It is also why it is the GHRP most often chosen for long-running research protocols.
What is the typical CJC-1295 + ipamorelin dose?
The most common community protocol is a ~100 mcg saturation dose of ipamorelin (roughly 1 mcg/kg). It is paired 1:1 with 100 mcg CJC-1295 (no-DAC) per injection, taken before bed on an empty stomach. This is community and vendor practice. No trial has set a dose for this stack used this way, so what follows is how people actually run it.
The saturation dose. For ipamorelin, the community view is a saturation dose of around 100 mcg (roughly 1 mcg/kg) per injection. Saturation means the receptors are already full. Reports describe less and less gain past that point, as the GH pulse does not get much bigger. Pushing well above it (300 mcg-plus, over long periods) is where cortisol and prolactin are described as starting to rise. Ipamorelin otherwise spares those. More is not better here. It is about filling the receptors, not filling a tank.
The classic pairing. The standard pattern is 100 mcg ipamorelin plus 100 mcg CJC-1295 (no-DAC) per shot, both drawn from the same blend. Some people run 100/200.
Worked mixing example. Take a 5 mg (5,000 mcg) blend vial and mix it with 2 mL of bacteriostatic water. That gives 2,500 mcg per mL, or 250 mcg per 0.1 mL. On a U-100 insulin syringe (100 units = 1 mL), 0.1 mL is the 10-unit mark. So a 100 mcg draw sits at the 4-unit mark (0.04 mL = 100 mcg). Add 0.5 mL more water (2.5 mL total) and the maths changes to 2,000 mcg/mL. A 100 mcg draw is then at the 5-unit mark. Always work out the unit mark for your own vial size and water volume. Do not reuse a number from a different mix.
Timing. Two rules lead the reported practice. First, dose before bed, so the pulse lands on top of the natural GH surge as you fall asleep. Second, dose on an empty stomach. That means at least two hours after your last meal, and ideally no food for 30 minutes after. Insulin and fat from food both blunt the GH pulse. Insulin holds back GH release, and fat drives up somatostatin. A single shot before bed is the most common protocol. People aiming at body composition add a second pulse (fasted in the morning, or after a workout), or a third across the day.
If you use the DAC version instead, the logic flips. The usual dose is roughly 1 to 2 mg once or twice a week for the steady level. Daily ipamorelin shots are often added on top for the pulse.
Cycling. Common patterns are 5 days on and 2 off, or 8 to 12 weeks on with 4 weeks off. The aim is mostly to stop the receptors becoming less responsive. These schedules are habit rather than trial-tested. If you are new to drawing and dosing peptides, how to reconstitute and dose walks through the practical side. Peptide stacking covers how this fits with other compounds.
What does the research timeline for this stack look like?
The effect builds slowly. It is not a switch. Here is the timeline, with the trial-backed science kept apart from what users report:
- Right away (the pulse): the GH pulse itself comes quickly. For ipamorelin, a human study of how the drug rises and clears in the blood found a GH peak around 40 minutes after the dose (Gobburu et al. 1999). Levels head back toward baseline within a couple of hours. A mild head-rush or facial flush shortly after injecting is common, and it usually passes in minutes.
- Weeks 2 to 4 (user reports): users report mild water retention. Some also get tingling in the hands or feet at higher doses.
- Weeks 4 to 12 (mechanism plus user reports): IGF-1 is the growth factor made in response to GH, and it carries out much of GH's work. User blood tests describe roughly a 20 to 30% IGF-1 rise at saturation dosing. People use this as an informal "is it working" check. This figure comes from users, not from a controlled trial of the stack.
- Beyond 12 weeks: there is no published human safety data past this point. See the safety notes below.
Whatever you see stays within the body's natural range. The stack boosts your own pulses, inside the pituitary's ceiling. It does not flood the system the way injected HGH does. Any vendor promising HGH-level results from a secretagogue stack is claiming more than the science supports.
What are the side effects of CJC-1295 + ipamorelin?
Reported side effects are mostly mild and linked to GH. In its one completed human trial, ipamorelin was well tolerated (Beck et al. 2014). Commonly reported effects:
- Facial flushing and a head-rush in the first 5 to 15 minutes after injecting. This is common, mostly put down to the CJC-1295 part, and usually gone within half an hour.
- Water retention and, at higher or longer doses, tingling or numbness in the hands and fingers. This is the classic GH fluid effect. It is the same thing behind the carpal-tunnel-like symptoms reported with GH. Reports describe it easing at lower doses.
- Injection-site reactions: mild redness or itching, common and short-lived.
- A small rise in appetite in some reports. Ipamorelin still acts on the ghrelin (hunger) receptor, so some hunger is plausible. It is described as far milder than with GHRP-6.
Selectivity is the headline. Because ipamorelin is selective, the stack does not carry the cortisol, prolactin and strong hunger of GHRP-2 or GHRP-6.
Things to know before a long protocol:
- The blend itself has not had its own trial. The way it works is well founded. The boost is shown in pig studies and small human studies pairing GHRH with a GHRP. But this exact CJC-1295-plus-ipamorelin blend has never been through a formal trial of its own. The body-composition numbers people quote come from users, not from a registration study (the kind of trial used to get a drug approved).
- Insulin sensitivity can drift when GH stays high for a long time. GH works against insulin's blood-sugar-lowering action. So high GH kept up over months is linked to rises in fasting blood sugar and HbA1c (a measure of average blood sugar). It is a useful marker to check with blood tests in any long protocol.
- Long-term safety data is thin. There is no published human data beyond roughly 12 weeks of continuous use of these compounds. The years-long "cruise" protocols some users run are uncharted.
- The IGF-1 and cancer question is in theory, but worth knowing. Anything that raises IGF-1 over the long term carries a question mark. A large UK Biobank study of ~394,000 people (Knuppel et al. 2020) looked at IGF-I levels in the blood. Higher levels were linked to a small rise in colorectal and prostate cancer risk (a hazard ratio of around 1.08 per 5 nmol/L). That is a link with IGF-1 levels in general, not direct evidence about these peptides. There is no long-term cancer data on CJC-1295 or ipamorelin either way.
- Ipamorelin's one Phase 2 efficacy trial missed its goal. Its only completed human efficacy study was in postoperative ileus, a stalled gut after surgery. It missed its main target (Beck et al. 2014), though it was well tolerated. The body-composition, sleep and anti-ageing uses that drive demand have never been through a completed human efficacy trial. The mechanism is well founded. The evidence for these uses comes from users.
Markers researchers track in the literature are IGF-1 (the direct marker of GH activity), fasting blood sugar and HbA1c. Under high long-term dosing, they also track prolactin and morning cortisol as a selectivity check.
Who researches the CJC-1295 + ipamorelin stack?
The stack is mainly researched in the GH peptide, recovery and longevity communities. These are the groups drawn to it:
- Lifters and bodybuilders, who prefer working with the body's own GH system over injecting GH. The reasons are cost, and keeping the natural pulses.
- Biohackers and longevity-minded researchers, who prefer the pulse pattern of a secretagogue over the flat line of injected HGH or oral MK-677. Their view is that keeping the natural rhythm is the more cautious long game.
- Sleep and recovery-focused researchers, including busy professionals, who run a single pulse before bed and nothing more.
Two groups it does not suit. For a drug-tested athlete, both peptides are on the WADA Prohibited List at all times. And alongside injected HGH or MK-677, the stack is mostly redundant. HGH skips the pituitary entirely, and MK-677 hits the same receptor as ipamorelin.
Referenced products
Take the 2-minute protocol quiz for a recommendation tailored to you.
Build your stackFrequently asked questions
Should CJC-1295 and ipamorelin be run together or one at a time?
Together. They are not competing options. They act on different receptors, and together they release more GH than either one alone. One on its own covers only part of the effect. That is why the pre-mixed blend exists.
What is the difference between CJC-1295 with DAC and without DAC?
DAC binds the peptide to albumin, a blood protein, and stretches its half-life to 5.8 to 8.1 days. That gives a steady, week-long "GH bleed". No-DAC (Mod GRF 1-29) clears in about 30 minutes and gives a short, sharp pulse. The no-DAC form pairs cleanly with ipamorelin and keeps the natural pulse pattern. It is the version the stack was designed around.
What is the typical dose?
Community practice centres on a ~100 mcg saturation dose of ipamorelin per shot. It is usually paired 1:1 with 100 mcg of CJC-1295 no-DAC, taken before bed on an empty stomach (at least two hours after food). Above ~100 mcg, ipamorelin adds little extra GH, and it is described as putting its clean, selective profile at risk. These are community protocols, not trial-tested doses.
Why ipamorelin instead of GHRP-2 or GHRP-6?
Selectivity. Ipamorelin releases GH without the cortisol, prolactin and strong hunger linked to the older GHRPs (Raun et al. 1998). That is what makes it the one most often chosen for long-running research protocols.
Does this match HGH?
No. The CJC-1295 and ipamorelin stack boosts your body's own GH pulses, within the pituitary's ceiling. That is a rise within the natural range, not the far-above-normal flood of injected HGH. Any claim of HGH-level results is more than the science supports.
Is it safe long-term?
That is not yet known. There is no published human safety data past about 12 weeks of continuous use. The main open questions are drift in insulin sensitivity, and the theoretical IGF-1 link over years of use. The literature flags IGF-1, blood sugar and HbA1c as the markers to check in any long-term protocol.
Does timing of day matter?
Before bed and on an empty stomach is the standard pattern. The pulse then lines up with the natural night-time GH surge. Insulin and fat from a recent meal blunt the response. Reported practice is to wait at least two hours after eating, and ideally 30 minutes before eating again.
Sources (9)›
- 1.Teichman et al. CJC-1295 GH/IGF-1 stimulation, JCEM 2006 pubmed.ncbi.nlm.nih.gov ↗
- 2.Ionescu & Frohman, CJC-1295 pulsatility, JCEM 2006 pubmed.ncbi.nlm.nih.gov ↗
- 3.Jetté et al. CJC-1295 GRF receptor activation, Endocrinology 2005 pubmed.ncbi.nlm.nih.gov ↗
- 4.Raun et al. Ipamorelin, the first selective GH secretagogue, Eur J Endocrinol 1998 pubmed.ncbi.nlm.nih.gov ↗
- 5.Gobburu et al. Ipamorelin PK/PD in human volunteers, Pharm Res 1999 pubmed.ncbi.nlm.nih.gov ↗
- 6.Beck et al. Ipamorelin Phase 2 in postoperative ileus, Int J Colorectal Dis 2014 pubmed.ncbi.nlm.nih.gov ↗
- 7.Bowers et al. GHRH + GHRP synergy in healthy men, JCEM 1990 pubmed.ncbi.nlm.nih.gov ↗
- 8.Jorgensen et al. GHRH + GHS co-administration, 2001 pubmed.ncbi.nlm.nih.gov ↗
- 9.Knuppel et al. Circulating IGF-I and risk of 30 cancers (UK Biobank), Cancer Research 2020 pubmed.ncbi.nlm.nih.gov ↗